


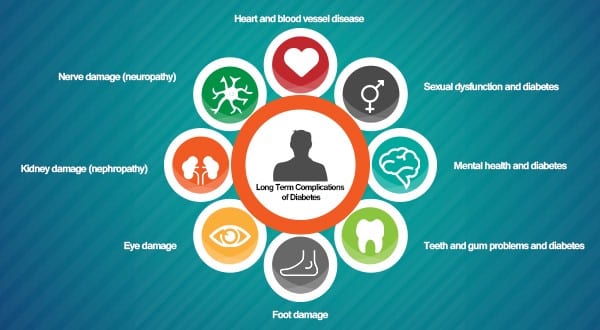
Complications of diabetes are health problems that develop when high blood glucose, insulin problems, and related risk factors strain blood vessels, nerves, and organs. They can happen in both type 1 and type 2 diabetes. Some develop fast and need urgent care, while others build quietly over years and may not cause symptoms until damage is harder to reverse.
This matters because diabetes is not only a blood sugar disorder. It can affect the eyes, kidneys, nerves, heart, brain, feet, skin, digestion, and infection risk. Knowing the main patterns, the warning signs, and the usual follow-up checks can help people spot trouble earlier and plan care more deliberately.
Key Takeaways
- Acute problems like severe low blood sugar, diabetic ketoacidosis, and hyperosmolar crisis can become emergencies quickly.
- Long-term issues most often involve the eyes, kidneys, nerves, heart, blood vessels, and feet.
- Symptoms may include blurry vision, numbness, swelling, chest pain, foot sores, recurring infections, or confusion.
- Risk rises with longer diabetes duration, higher glucose exposure, high blood pressure, abnormal cholesterol, smoking, and missed follow-up.
- Many early changes are silent, so screening often finds problems before symptoms do.
Complications of Diabetes: Acute and Long-Term Patterns
The two broad groups are acute metabolic emergencies and chronic organ damage. Acute problems can develop over hours or days. Chronic problems usually reflect months to years of exposure to high glucose, high blood pressure, abnormal cholesterol, inflammation, and tobacco use.
High blood sugar can injure the lining of blood vessels and change how nerves send signals. It can also force the kidneys to work harder and affect how well the retina at the back of the eye handles oxygen. Over time, this is why diabetes can feel like one diagnosis but behave like a whole-body condition.
Acute complications
The main acute complications are severe hypoglycemia, diabetic ketoacidosis, and hyperosmolar hyperglycemic state. Severe hypoglycemia means blood sugar drops low enough to cause confusion, seizure, or loss of consciousness. Diabetic ketoacidosis, or DKA, happens when the body lacks enough insulin and starts breaking down fat too fast, producing ketones. Hyperosmolar hyperglycemic state, or HHS, usually involves very high glucose, marked dehydration, and mental status changes. These problems need urgent medical assessment.
Chronic complications
Chronic complications are often grouped as microvascular and macrovascular disease. Microvascular means small-vessel damage, mainly affecting the eyes, kidneys, and nerves. Macrovascular means large-vessel disease involving the heart, brain, and circulation in the legs. For broader background on the condition itself, browse the Diabetes Condition Hub.
Why it matters: Eye, kidney, and nerve damage may begin before symptoms do.
Which Problems Clinicians Watch Most Closely
A simple answer to the common major complications question is this: cardiovascular disease, kidney disease, eye disease, nerve damage, and foot disease are the core areas clinicians watch most closely. There is no single most common complication for every person, because risk changes with age, diabetes type, duration, blood pressure, kidney health, smoking, and other conditions.
Heart and blood vessel disease often drives the most serious outcomes. Kidney disease can remain silent until lab tests change. Nerve damage may start as tingling or burning, or it may reduce feeling so much that a foot injury goes unnoticed. Eye disease can progress quietly until vision changes appear. Foot problems sit at the intersection of nerve damage, poor circulation, pressure points, and infection.
| Category | Common examples | What you may notice |
|---|---|---|
| Small-vessel damage | Diabetic retinopathy, nephropathy, neuropathy | Blurry vision, burning pain, numbness, or no symptoms at first |
| Large-vessel disease | Coronary disease, stroke, peripheral artery disease | Chest pressure, shortness of breath, calf pain, weakness, or speech trouble |
| Related complications | Foot ulcers, skin infections, gum disease, gastroparesis, erectile problems | Sores, redness, early fullness, nausea, gum bleeding, or recurring infections |
Other complications also matter. Diabetes can increase the risk of gum disease, skin problems, slower wound healing, and frequent infections. It can also contribute to digestive complications such as gastroparesis, which means delayed stomach emptying. Sexual dysfunction can occur in both men and women. These issues may not seem as dramatic as stroke or kidney failure, but they can strongly affect function, sleep, nutrition, and daily comfort.
Symptoms and Warning Signs Worth Noticing
Symptoms depend on which organ system is affected, and some people have none until screening detects a change. Some complications of diabetes cause pain or obvious changes. Others stay silent until an eye exam, urine test, blood test, foot exam, or blood pressure check shows a problem.
That is why clinicians ask about both new symptoms and routine monitoring. A normal day does not rule out early retinopathy or kidney disease. By contrast, a new foot blister, sudden blurred vision, or repeated infections can be the first visible clue that glucose or circulation needs closer review.
- Vision changes — blur, floaters, dark spots, or trouble seeing at night
- Numbness or burning — tingling, pain, or loss of feeling in feet or hands
- Kidney clues — swelling, rising blood pressure, or lab changes before symptoms
- Foot changes — blisters, calluses, cuts, redness, drainage, or slow-healing sores
- Infection patterns — repeated skin, gum, urinary, or yeast infections
- Digestive slowdown — early fullness, nausea, bloating, vomiting, or constipation
- Circulation problems — cold feet, color change, leg pain with walking, or nonhealing wounds
Mental and mood changes can happen too. Very high or very low glucose may cause irritability, trouble concentrating, unusual fatigue, or confusion. Severe changes in alertness, deep rapid breathing, chest pain, or one-sided weakness are not routine symptoms and should be treated as urgent.
What Changes the Risk and Timeline
The timeline for complications of diabetes is not fixed. Some people have eye, kidney, or nerve changes near the time type 2 diabetes is diagnosed because high glucose may have been present for years before diagnosis. In type 1 diabetes, acute problems such as DKA can happen early if insulin is interrupted or illness increases insulin needs, while chronic complications more often relate to longer duration.
Risk rises when several factors cluster together. Higher average glucose is important, but it is not the only driver. High blood pressure, abnormal cholesterol, chronic kidney disease, sleep problems, older age, and limited access to regular follow-up can all change the pace. Recurrent severe lows or repeated dehydration can add risk in different ways.
There is also no single chart that predicts exactly when retinopathy, nephropathy, or neuropathy will appear. Two people with the same diabetes type may have very different paths. That is why screening recommendations are based on risk patterns and diabetes duration, not symptoms alone.
Pregnancy needs closer review
Pregnancy can change how diabetes complications are monitored. Existing eye or kidney disease may need closer follow-up, and blood pressure and glucose management usually require tighter coordination with the care team. People planning pregnancy or already pregnant should review current complications and monitoring schedules early, because pregnancy can change both short-term and long-term risk.
Practical Steps to Lower Risk and Plan Follow-Up
Preventing complications of diabetes usually depends on steady follow-up and day-to-day habits, not one perfect number. The aim is to reduce ongoing strain on blood vessels, nerves, and organs while catching new problems early enough to respond.
People often ask for one forbidden-food list. In practice, complication risk tracks the overall pattern more than a single meal. Glucose trends, blood pressure, cholesterol, tobacco use, activity, sleep, medication access, and routine screening all interact. Food choices matter, but they work best as part of a broader plan.
- Track patterns, not guesses — note highs, lows, illness, and new symptoms
- Keep screening visits — eye exams, kidney tests, foot checks, and blood pressure review
- Protect feet daily — look for cuts, blisters, color change, or swelling
- Review heart risk — ask about lipids, smoking, sleep, and circulation symptoms
- Report infections early — skin, gum, urinary, or foot changes deserve attention
- Bring a symptom list — numbness, vision change, swelling, pain, or digestive slowing
- Plan for transitions — illness, surgery, travel, and pregnancy can change risk
Routine labs and exams matter because early kidney and eye changes are often silent. A urine test may detect protein before swelling appears. A dilated eye exam may show retinopathy before vision drops. Foot exams can find pressure points or loss of sensation that a person has adapted to and stopped noticing.
If a complication is identified, the next step is usually not the same for everyone. The care plan may focus on tighter glucose review, blood pressure management, cholesterol treatment, foot protection, smoking cessation, or referral to eye, kidney, vascular, or nerve specialists. The goal is to understand what is affected, how advanced it seems, and what can slow further injury.
For broader self-education, browse the Diabetes Category, which collects diabetes reading in one place. If treatment categories come up during follow-up, the Diabetes Product Category is a browsable hub of diabetes therapies.
Prescription details may need confirmation with the prescribing clinician.
Quick tip: Bring shoes and socks into the exam room if foot symptoms are new.
When to Seek Prompt Medical Care
Get prompt medical care when symptoms suggest an acute metabolic problem, a heart or brain event, a fast-moving infection, or a worsening foot wound. Waiting can turn a manageable problem into an emergency.
- Severe low glucose — seizure, loss of consciousness, or inability to swallow safely
- Possible DKA or HHS — vomiting, deep breathing, severe thirst, marked sleepiness, or confusion
- Heart or stroke symptoms — chest pressure, sudden shortness of breath, facial droop, weak arm, or trouble speaking
- Sudden eye symptoms — abrupt vision loss, large floaters, or a dark curtain over vision
- Serious foot or skin infection — spreading redness, pus, fever, blackened tissue, or rapidly worsening pain
Do not rely on home monitoring alone if a person is hard to wake, cannot keep fluids down, has rapid breathing, or seems acutely confused. Those patterns can signal dehydration, severe infection, stroke, or dangerous glucose extremes. The same is true for a foot wound that is deep, foul-smelling, or worsening despite basic wound care.
Further reading helps connect symptoms, screening, and long-term risk. In general, complications are easier to slow when they are found early than when they are first noticed during a crisis.
Authoritative Sources
- For a broad public-health summary, see CDC Diabetes Complications.
- For a plain-language overview of common issues, review MedlinePlus Diabetes Complications.
- For risk-reduction advice from a major medical group, read American Diabetes Association Complications.
This content is for informational purposes only and is not a substitute for professional medical advice.











