


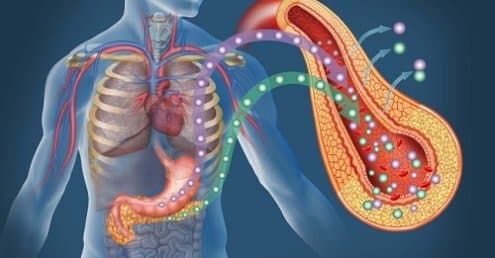
Insulin and glucagon are pancreatic hormones that work as a blood glucose balancing system. Insulin usually lowers blood glucose after meals by helping glucose move from the bloodstream into cells and storage sites. Glucagon usually raises blood glucose between meals by telling the liver to release stored glucose. This back-and-forth matters because the brain, muscles, and organs need a steady fuel supply.
This article explains where these hormones are made, how they work, and why their relationship matters in diabetes. It also clarifies common questions about glucagon, insulin, food, symptoms, and when to bring glucose patterns to a clinician.
Key Takeaways
- Shared source: Both hormones come from pancreatic islets.
- Different cells: Beta cells make insulin; alpha cells make glucagon.
- Opposite direction: Insulin lowers glucose; glucagon raises it.
- Liver role: Glucagon mainly acts on the liver.
- Safety signal: Repeated highs, lows, or confusion need medical review.
Insulin and Glucagon Function in Plain Language
The simplest way to understand insulin and glucagon function is to view the hormones as paired signals, not separate switches. Insulin responds most strongly when blood glucose rises, such as after eating carbohydrates. Glucagon responds most strongly when blood glucose falls, such as between meals, overnight, or during longer fasting periods.
They are often called antagonistic hormones because they tend to push glucose in opposite directions. That does not mean one hormone is good and the other is bad. Both are needed. A healthy body uses each signal at the right time, then adjusts as food intake, activity, stress, sleep, and illness change energy needs.
| Hormone | Main trigger | Main source | Major target | Blood glucose effect |
|---|---|---|---|---|
| Insulin | Rising blood glucose after food | Beta cells in pancreatic islets | Liver, muscle, and fat tissue | Helps glucose leave the blood for use or storage |
| Glucagon | Falling blood glucose between meals | Alpha cells in pancreatic islets | Mainly the liver | Helps the liver release and make glucose |
Both are peptide hormones, meaning their structures are built from amino acid chains. Their structures differ enough to fit different receptors, which are protein sensors on cells. That difference lets insulin and glucagon send distinct messages even though both circulate in the bloodstream.
Why it matters: Blood glucose balance depends on timing, liver storage, and tissue response.
Where Insulin and Glucagon Are Produced
Insulin and glucagon are produced by endocrine cells inside the pancreas. More precisely, they come from the islets of Langerhans, which are small hormone-making clusters scattered through the pancreas.
Beta cells make insulin. Alpha cells make glucagon. This is why questions such as where is glucagon produced, where are insulin and glucagon produced, and which organ makes insulin usually point back to the pancreas. For more context on this organ’s role in diabetes, review Pancreas And Diabetes.
The pancreas does not manage blood glucose alone. The liver stores glucose as glycogen and releases glucose when needed. Muscle and fat tissue also respond to insulin. If you want a deeper look at insulin’s role after glucose enters the blood, see Insulin And Glucose.
Yes, insulin and glucagon are hormones. They are endocrine hormones because they are released into the bloodstream and act on tissues beyond the cells that made them. Their effects also interact with other hormones, including epinephrine, cortisol, growth hormone, amylin, and incretin hormones.
What Happens After Eating, Fasting, and Activity
After a meal
After eating, digested carbohydrates break down into glucose and move into the bloodstream. Rising glucose prompts beta cells to release insulin. Insulin helps many cells take up glucose and supports storage of extra glucose as glycogen in the liver and muscles. For a broader look at insulin’s body-wide effects, read What Insulin Does.
Insulin also helps reduce glucose release from the liver when enough fuel is already available. This prevents blood glucose from continuing to rise after the meal has been absorbed. The exact response varies by meal size, carbohydrate type, activity level, sleep, stress, and medication use.
Between meals
Between meals, blood glucose tends to fall as cells keep using fuel. In response, alpha cells release more glucagon. Glucagon tells the liver to break down glycogen, a storage form of glucose. It can also support gluconeogenesis, which means making new glucose from non-carbohydrate building blocks.
The main glucagon target organ is the liver. Muscle tissue stores glycogen too, but it mainly uses that fuel locally during activity. The liver is better suited to release glucose back into the bloodstream for the rest of the body.
During activity, stress, or illness
Physical activity can lower glucose because working muscles use more fuel. Some intense activity, stress, or illness can raise glucose because stress hormones signal the body to make more fuel available. This is one reason glucose patterns can look different from day to day, even when meals seem similar.
If you track readings, units may appear as mg/dL or mmol/L depending on the meter, lab, or country. This converter can help compare common glucose units, but it does not define personal targets or replace clinical guidance.
Blood Glucose Unit Converter
Convert glucose readings between mg/dL and mmol/L without changing the clinical value.
These calculations are for education only and do not replace clinical advice, diagnosis, or treatment. Always confirm medical decisions with a qualified healthcare professional.
Why the Glucagon and Insulin Relationship Matters in Diabetes
In diabetes, the glucagon and insulin relationship can become less coordinated. In type 1 diabetes, the body makes little or no insulin because immune injury affects beta cells. In type 2 diabetes, the body may resist insulin’s effects, and beta-cell function may decline over time. Some people with diabetes also have glucagon responses that do not match the body’s actual glucose needs.
This matters because blood glucose is shaped by both how much glucose enters the blood and how well tissues respond to hormone signals. Insulin resistance, changes in pancreatic function, liver glucose release, food intake, and medications can all affect patterns. For more background, see Insulin Hormone Function.
Low blood glucose, also called hypoglycemia, can occur when glucose available in the blood falls below what the body needs. Symptoms may include shakiness, sweating, hunger, confusion, fast heartbeat, or weakness. Severe symptoms such as fainting, seizures, inability to swallow safely, or marked confusion need urgent medical help.
High blood glucose can cause thirst, frequent urination, fatigue, blurry vision, or recurrent infections. Very high levels with vomiting, abdominal pain, deep breathing, fruity-smelling breath, or severe drowsiness can signal a medical emergency. People using insulin or medicines that can cause lows should ask their clinician about prevention, monitoring, and when rescue glucagon may be appropriate.
CanadianInsulin.com is a prescription referral platform, and prescription details may be confirmed with a prescriber where required. Dispensing and fulfilment are handled by licensed third-party pharmacies where permitted. This service context does not replace individualized medical advice about insulin, glucagon, or glucose targets.
Food Questions, Low Glucose, and Common Myths
Food questions often come up when people learn about these hormones. No single fruit, morning drink, or avoided food controls A1C by itself. A1C reflects longer-term glucose exposure. Portions, total carbohydrate intake, medication timing, activity, sleep, and health conditions all matter.
A peanut butter sandwich is sometimes discussed for low blood sugar because it contains carbohydrate, fat, and protein. However, fat and protein can slow digestion, so it may not be the fastest option for an urgent low. People at risk for hypoglycemia should follow the low-glucose plan provided by their care team, especially if they use insulin or medicines that can cause lows.
There is also no universal number-one worst food for blood sugar. Highly concentrated sugars can raise glucose quickly, but the real effect depends on portion size, timing, other foods in the meal, activity, and medications. A registered dietitian or diabetes clinician can help personalize carbohydrate targets, especially during pregnancy, kidney disease, gastroparesis, eating disorder recovery, or recurrent lows.
Morning drink advice should also be individualized. Water, unsweetened drinks, and usual meal routines may affect people differently depending on glucose trends and medications. If morning readings are often high or low, bring the pattern to a clinician rather than relying on a single food rule.
How Glucagon Differs From Related Hormones and Medicines
Glucagon is not the same as glucagon-like peptide-1, often shortened to GLP-1. GLP-1 is an incretin hormone released from the gut after eating. It helps coordinate meal-related insulin release and other digestive signals. The names sound similar, but the hormones have different sources, receptors, and effects.
Diabetes medicines can affect glucose through many pathways. Some support insulin action, some affect kidney glucose handling, and some influence incretin pathways. Insulin products replace or supplement insulin directly. Glucagon rescue products are used for severe low blood glucose in specific situations.
If you are comparing the two core hormones, the practical difference is direction and timing. Insulin helps manage glucose when fuel is available. Glucagon helps protect against shortage when glucose is falling. For a dedicated comparison, see Insulin Vs Glucagon.
Some readers also want to understand product categories after learning the physiology. The Diabetes Product Category is a browseable collection, not a substitute for clinician guidance. Medication decisions should be made with a prescriber because risks, benefits, and monitoring needs vary by person.
Practical Questions to Bring to a Clinician
Understanding the physiology is useful, but personal glucose care depends on your medical history. Bring actual readings, symptoms, meal timing, activity patterns, and a current medication list to appointments. This is especially important if you use insulin, have repeated hypoglycemia, or notice symptoms that do not match your meter or continuous glucose monitor.
- Pattern review: Ask which readings matter most.
- Low glucose plan: Review safe treatment steps.
- Meal effects: Discuss carbohydrate portions and timing.
- Activity changes: Ask how exercise may shift readings.
- Medication timing: Review medicines that may cause lows.
- Sick days: Ask when illness needs urgent review.
Do not stop, start, or change diabetes medicines based only on general physiology. Hormone balance is one part of care. Kidney function, pregnancy status, age, other medicines, eating patterns, and past hypoglycemia also shape safe decisions. A broader Diabetes Articles collection can help you prepare general education questions before a visit.
Authoritative Sources
These sources support the medical framing of this article and can help readers verify hormone physiology and diabetes safety basics.
- The Endocrine Society overview of pancreas hormones explains pancreatic hormone roles.
- The NIDDK overview of diabetes basics describes diabetes types and blood glucose problems.
- The American Diabetes Association hypoglycemia resource reviews low blood glucose symptoms and safety steps.
Learning how insulin and glucagon work can make glucose readings easier to discuss with a care team. It also helps explain why meals, fasting, activity, illness, and medications can all change blood glucose in different ways.
This content is for informational purposes only and is not a substitute for professional medical advice.











