


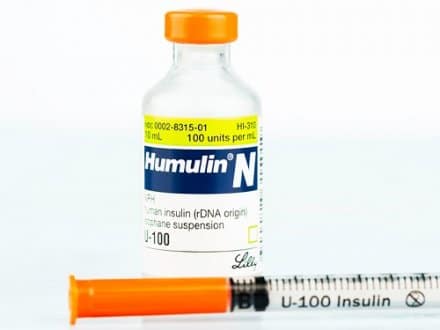
Basal insulin is background insulin that helps keep glucose steadier between meals and overnight. Understanding what is basal insulin matters because it explains why some insulin works slowly for many hours, while mealtime insulin acts quickly around food. Basal dosing is usually planned with a clinician, then adjusted from glucose patterns, fasting readings, hypoglycemia risk, and the rest of your diabetes treatment plan.
Another name for basal insulin is background insulin. It does not replace meal coverage when rapid-acting insulin is needed, and it is not meant to correct every high reading by itself. Its main job is to cover baseline insulin needs when you are not eating.
Key Takeaways
- Background role: Basal insulin covers fasting and between-meal needs.
- Main examples: NPH, glargine, detemir, and degludec are common options.
- Timing differs: Some formulations peak, while others have flatter profiles.
- Dosing is individualized: Weight, glucose patterns, meals, activity, and safety all matter.
- Bolus pairing: Many people use basal with mealtime insulin in a basal-bolus plan.
What Basal Insulin Does in the Body
Basal insulin provides a slow, steady insulin supply to limit glucose release from the liver. The liver naturally releases glucose during fasting, including overnight. Without enough background insulin, fasting glucose may rise even when no food was eaten.
This is why the basal dose meaning is different from a meal dose. A basal dose aims to hold glucose relatively steady when food is not the main driver. A bolus dose targets carbohydrates in a meal or corrects a high reading under a care plan.
Basal insulin is used in different ways across diabetes care. People with type 1 diabetes generally need background and mealtime insulin because the body makes little or no insulin. Some people with type 2 diabetes use basal insulin when other treatments do not provide enough glucose control. The exact plan depends on diagnosis, glucose targets, other medicines, lifestyle, and clinical history.
For a deeper comparison of background and meal coverage, see Basal vs Bolus Insulin. That page explains how the two roles fit together in daily diabetes management.
Types of Basal Insulin and How Long They Last
The main types of basal insulin include intermediate-acting and long-acting formulations. NPH is intermediate-acting and has a more noticeable peak. Glargine, detemir, and degludec are longer-acting options designed to provide smoother background coverage.
People often ask whether basal insulin is long acting. Many basal products are long acting, but not all. NPH is usually described as intermediate-acting because it starts, peaks, and wears off sooner than many modern long-acting insulins. This difference can affect injection timing, hypoglycemia risk, and how clinicians adjust the plan.
| Category | Common Examples | Typical Peak Pattern | General Duration Pattern |
|---|---|---|---|
| Intermediate-acting | NPH insulin | More noticeable peak | Often shorter than long-acting options |
| Long-acting glargine U-100 | Lantus, Basaglar | Minimal peak for many people | Designed for about daily background coverage |
| Long-acting detemir | Levemir | Relatively flat for many people | May require individualized timing |
| Ultra-long acting | Tresiba | Minimal peak for many people | Designed for extended background action |
| Concentrated glargine | Toujeo | Flatter profile for many people | Designed for prolonged background coverage |
These are broad categories, not interchangeable instructions. Your response can vary with dose size, injection timing, kidney function, activity, illness, and other medicines. Product labels also differ in how they describe use, warnings, and administration.
For a closer look at long-acting insulin names and timing, review Long-Acting Insulin Names. If your plan includes NPH, Intermediate-Acting Insulin Types explains why its peak matters.
Basal vs Bolus Insulin: The Practical Difference
Basal insulin covers background needs, while bolus insulin covers meals and corrections. This is the core difference in basal vs bolus insulin. Basal acts slowly over many hours. Bolus insulin is usually rapid-acting or short-acting and is timed around food or a correction plan.
In plain terms, basal is the foundation and bolus handles spikes. If fasting readings rise overnight, clinicians may review basal timing, dose, food, alcohol, illness, or dawn phenomenon. If glucose rises mainly after meals, the issue may involve carbohydrate counting, meal timing, bolus timing, or correction factors rather than basal alone.
The basal-bolus meaning is a treatment structure that uses both types to mimic normal insulin patterns more closely. It is common in type 1 diabetes and sometimes used in type 2 diabetes when more intensive insulin therapy is needed. A basal-bolus plan may involve one or more background injections plus mealtime doses.
Why it matters: Adjusting basal to fix meal spikes can raise overnight hypoglycemia risk.
What Is Bolus Insulin?
Bolus insulin is insulin taken for meals or correction doses. It helps manage glucose increases after eating carbohydrates. Some plans use insulin-to-carbohydrate ratios, correction factors, and target ranges to estimate a dose. These numbers are personal and should come from a clinician or diabetes care team.
For examples of how dose planning is commonly discussed, see the Insulin Dosage Chart. Use it as educational context, not as a substitute for individualized dosing advice.
Basal-Bolus Ratios and Dose Planning
Basal-bolus ratios describe how total daily insulin is split between background and mealtime needs. Some people use a near-even split, while others need more or less basal depending on food patterns, insulin sensitivity, physical activity, and glucose trends. There is no single ratio that fits everyone.
When people ask how to calculate basal insulin dose, clinicians often start with broad frameworks. A plan may use body weight, current glucose readings, A1C, insulin history, and hypoglycemia risk. From there, the dose is usually titrated in small steps based on fasting glucose and safety. Do not change insulin doses without guidance from your prescriber or diabetes team.
Weight-based dosing can help create a cautious starting point. However, weight is only one factor. Older adults, people with kidney disease, people with irregular meals, and those with frequent low glucose may need more conservative adjustments. Pregnancy, steroid use, acute illness, and major activity changes also require clinician review.
Glucose units can also create confusion when readings are shared between systems. This converter can help you compare mg/dL and mmol/L values for general record-keeping; it does not recommend insulin doses.
Blood Glucose Unit Converter
Convert glucose readings between mg/dL and mmol/L without changing the clinical value.
These calculations are for education only and do not replace clinical advice, diagnosis, or treatment. Always confirm medical decisions with a qualified healthcare professional.
Example: Pattern Review, Not Self-Adjustment
Example: A person has stable bedtime readings but wakes up high most mornings. Their care team may review basal timing, overnight snacks, dawn phenomenon, injection technique, and missed doses. If another person wakes up low, the review may focus on evening activity, alcohol, delayed meal bolus effects, or an excessive background dose.
These examples show why patterns matter more than one reading. A single high or low may have many causes. Repeated trends are more useful for clinical decision-making.
Lantus and Other Basal Insulin Examples
Lantus is a basal insulin because it contains insulin glargine U-100, a long-acting insulin. Basaglar is also insulin glargine U-100. Toujeo contains concentrated insulin glargine U-300. Levemir contains insulin detemir, and Tresiba contains insulin degludec.
These long-acting insulin names are not simply brand labels. They may differ in concentration, duration profile, device format, and label instructions. Switching between products should be handled by a prescriber because unit needs and timing may not transfer in a simple one-to-one way for every patient or product.
People comparing products may find it helpful to review specific item formats. Examples include Lantus SoloStar Pens, Tresiba FlexTouch Pens, and Toujeo DoubleStar Pen. Product pages can help you identify formulation and device details, but clinical selection belongs with your care team.
CanadianInsulin.com operates as a prescription referral platform, and prescription details may be confirmed with the prescriber where required. Dispensing and fulfilment are handled by licensed third-party pharmacies where permitted.
Safety, Side Effects, and When to Seek Help
The most important basal insulin side effect is hypoglycemia, or low blood glucose. Symptoms may include shakiness, sweating, confusion, hunger, irritability, fast heartbeat, or weakness. Severe hypoglycemia can cause seizure, loss of consciousness, or injury and needs urgent help.
Other possible issues include injection-site reactions, skin thickening or pitting from repeated injections in one area, allergic reactions, and dosing errors. Rotating injection sites may reduce local skin problems. Using the same product name, concentration, and device as prescribed can help reduce confusion.
Several situations can change insulin needs. These include missed meals, vomiting, alcohol use, new exercise routines, steroid medicines, infection, surgery, pregnancy, and kidney function changes. If readings are repeatedly low, unusually high, or difficult to explain, contact your healthcare professional promptly.
Seek urgent medical care for severe low glucose, symptoms of diabetic ketoacidosis such as vomiting with high glucose or ketones, trouble breathing, severe dehydration, chest pain, or signs of a serious allergic reaction. Do not stop basal insulin without medical direction, especially if you have type 1 diabetes.
Quick tip: Keep a current insulin list with brand, concentration, device, and timing.
Common Practical Pitfalls
Basal insulin works best when the routine around it is clear. Many problems come from timing changes, missed doses, duplicate doses, or confusing similar-looking pens. Storage and injection technique can also affect how reliably insulin works.
- Chasing meal spikes: Basal is not a meal bolus replacement.
- Ignoring lows: Repeated hypoglycemia needs prompt clinical review.
- Switching products casually: Concentrations and instructions may differ.
- Skipping pattern notes: Bedtime and morning readings help show trends.
- Reusing one site: Rotation helps reduce skin changes.
- Changing during illness alone: Sick-day plans should be clinician-guided.
If you use multiple insulin types, label-reading matters. For broader unit and concentration context, see Insulin Conversions. This can help you understand terminology, although it should not be used to independently change a prescription.
Authoritative Sources
For official medication safety details, review the FDA prescribing information for insulin glargine. It outlines contraindications, warnings, and adverse reactions for that product.
The American Diabetes Association publishes annual clinical standards. Its Standards of Care in Diabetes discuss insulin use, treatment intensification, hypoglycemia, and individualized care goals.
For Canadian drug information, Health Canada provides a searchable Drug Product Database with product-specific records and monograph access when available.
Recap
Basal insulin is background insulin used to support glucose control between meals and overnight. Common basal insulin examples include NPH, glargine, detemir, and degludec, with different peak and duration patterns. Basal works differently from bolus insulin, so dose planning should consider fasting trends, meal coverage, activity, safety, and the full treatment plan.
For more diabetes education, browse the Diabetes Articles collection. You can also explore the Diabetes condition page for related navigation.
This content is for informational purposes only and is not a substitute for professional medical advice.











